Wrist Pain: Causes, Symptoms, Diagnosis, and Physiotherapy Management in Jatrabari, Dhaka | ADPORC

Wrist pain causes and physiotherapy treatment illustration

Wrist pain is a common upper-limb problem that can interfere with gripping, typing, writing, lifting objects, using a smartphone, opening containers, exercising or performing repetitive hand activities.

Some wrist problems develop gradually after repeated gripping, computer work, sports, manual tasks or prolonged loading. Others begin after a fall, twisting injury, sudden force or direct trauma. Depending on the underlying condition, wrist pain may occur together with swelling, stiffness, weakness, reduced grip strength, tingling or numbness.

The wrist is a complex region made up of several small bones, joints, ligaments, tendons, tendon sheaths and nerves. These structures allow the hand to move through multiple directions while also transferring force between the forearm and hand. Because many structures are located within a relatively small area, different wrist conditions can produce overlapping symptoms.

At Asia Digital Physiotherapy Orthopedic Rehabilitation Center (ADPORC), wrist rehabilitation is planned according to the patient's clinical assessment, pain pattern, movement restriction, grip strength, neurological findings and functional limitations. Treatment may include activity and load modification, therapeutic exercise, mobility training, progressive strengthening, tendon or nerve rehabilitation, manual therapy and other physiotherapy interventions according to clinical need.

Understanding Wrist Pain: A Structural Perspective

Wrist pain refers to discomfort arising from the wrist joint or the structures around it. Pain may occur on the thumb side, little-finger side, palm side or back of the wrist. In some conditions, symptoms may extend into the hand, fingers or forearm.

The wrist and surrounding region contain several clinically important structures:

  1. Radius and ulna at the distal forearm
  2. Eight carpal bones
  3. Radiocarpal and intercarpal joints
  4. Wrist ligaments
  5. Flexor and extensor tendons
  6. Tendon sheaths
  7. Triangular fibrocartilage complex (TFCC)
  8. Median, ulnar and radial nerves
  9. Carpal tunnel and other soft-tissue passages
  10. Muscles contributing to wrist, thumb and finger movement

Depending on the structure involved, wrist problems may produce sharp or aching pain, tenderness, swelling, stiffness, weakness, reduced grip strength, clicking, burning, tingling or numbness.

The location and behaviour of symptoms can help narrow down the possible cause, but they cannot establish a diagnosis by themselves.

Common Locations of Wrist Pain and What They May Mean

The location of wrist pain provides useful clues about which structures may require further assessment.

  1. Thumb-Side Wrist Pain:
    Pain around the radial or thumb side of the wrist is commonly associated with De Quervain’s Tenosynovitis.
    The pain may increase during gripping, lifting a child, twisting, opening containers, using a smartphone or moving the thumb repeatedly.
  2. Palm-Side Wrist Pain With Tingling or Numbness:
    Pain, burning, tingling or numbness around the palm side of the wrist and hand may suggest Carpal Tunnel Syndrome, particularly when symptoms affect the thumb, index and middle fingers.
    Symptoms often become noticeable at night or during prolonged typing, driving, holding a phone or other sustained hand activities.
    Carpal Tunnel Syndrome occurs when the median nerve becomes compressed within the carpal tunnel at the wrist.
  3. Little-Finger Side Wrist Pain:
    Pain on the ulnar or little-finger side of the wrist may involve structures such as the triangular fibrocartilage complex (TFCC), extensor carpi ulnaris tendon or other ulnar-sided wrist structures.
    Pain may increase during gripping, forearm rotation, pushing through the hand or weight-bearing activities.
  4. Pain at the Back of the Wrist:
    Dorsal wrist pain may occur with extensor tendon problems, ligament injuries, ganglion cysts or joint-related disorders.
    Some patients notice pain particularly during wrist extension, push-ups, weight training or prolonged loading through the hand.
  5. Wrist Pain After a Fall or Sudden Injury:
    Pain that begins immediately after falling onto the hand, twisting the wrist or sustaining direct trauma may indicate a sprain, ligament injury or fracture.
    Significant swelling, bruising, deformity or difficulty using the hand after trauma requires appropriate medical assessment.
  6. Wrist Pain With Clicking or Instability:
    Clicking, catching, painful rotation or a feeling that the wrist is unstable may occur with ligament or TFCC-related injuries.
    Clinical assessment is important because several different structures can produce mechanical wrist symptoms.
  7. Wrist Weakness or Difficulty Lifting the Hand:
    Marked weakness of wrist extension, particularly when a person cannot actively lift the wrist and fingers upward, suggests a neurological problem rather than a typical wrist-pain condition.
    One example is Wrist Drop, which is commonly associated with radial nerve dysfunction.
    Pain may or may not accompany Wrist Drop, so it should be evaluated as a neurological and functional problem rather than assumed to be a simple painful wrist disorder.

Common Causes of Wrist Pain

Wrist pain may originate from tendons, tendon sheaths, nerves, ligaments, cartilage, bones or joints. The following are several important causes.

  1. De Quervain’s Tenosynovitis:
    De Quervain’s Tenosynovitis affects tendons on the thumb side of the wrist, particularly the abductor pollicis longus and extensor pollicis brevis.
    Repeated thumb and wrist loading can irritate the tendon sheath and make tendon gliding painful. Patients commonly experience thumb-side wrist pain, swelling, reduced grip strength and discomfort during gripping, twisting or lifting.
    Related guide: De Quervain’s Tenosynovitis: Causes, Symptoms & Physiotherapy Treatment
  2. Carpal Tunnel Syndrome:
    Carpal Tunnel Syndrome (CTS) is a nerve compression condition involving the median nerve as it travels through the carpal tunnel at the wrist.
    Patients may experience numbness, tingling, burning discomfort, night symptoms, reduced grip strength or difficulty with fine hand activities. Some people also notice that they drop objects more frequently.
    Related guide: Carpal Tunnel Syndrome (CTS): Causes, Symptoms & Physiotherapy Treatment
  3. Wrist Sprain and Ligament Injury:
    A wrist sprain occurs when one or more ligaments are overstretched or injured.
    It may occur after a fall onto an outstretched hand, sudden twisting, sporting injury or other trauma. Symptoms can include pain, swelling, tenderness, reduced movement and difficulty gripping or loading through the hand.
    The severity of wrist ligament injuries varies, so significant traumatic symptoms require assessment to exclude fracture or major instability.
  4. Wrist Tendinopathy and Tenosynovitis:
    Several tendons cross the wrist to control hand and finger movement.
    Repetitive gripping, lifting, racket sports, gym training, manual work or sudden increases in activity may overload these tendons.
    Symptoms may include localized pain during wrist movement, tenderness along a tendon and discomfort during gripping or resisted movements.
  5. Triangular Fibrocartilage Complex (TFCC) Injury:
    The TFCC is an important stabilizing structure on the ulnar side of the wrist.
    Injury may occur after a fall, forceful rotation or repetitive loading. Patients may experience little-finger-side wrist pain, clicking, weakness or pain when rotating the forearm, gripping or pushing through the hand.
  6. Ganglion Cyst:
    A ganglion cyst is a fluid-filled lump that commonly appears around the wrist or hand.
    Some ganglion cysts cause no symptoms, while others may produce localized discomfort, pressure, restricted movement or pain during wrist loading.
    A new or changing lump around the wrist should be appropriately assessed rather than assumed to be a ganglion without examination.
  7. Wrist Osteoarthritis and Other Joint Disorders:
    Degenerative or inflammatory joint conditions can produce deeper wrist pain, stiffness, swelling and reduced range of motion.
    Previous fractures or significant wrist injuries may also contribute to post-traumatic joint changes later.
  8. Wrist Fracture and Post-Traumatic Pain:
    Fractures around the distal radius or carpal bones can occur after falls or other significant trauma.
    After the fracture has healed, some patients continue to experience stiffness, weakness, reduced grip strength or difficulty returning to normal hand use and may require rehabilitation.
    Persistent pain after trauma should not be assumed to be a simple sprain without appropriate assessment.
  9. Nerve-Related or Referred Wrist Pain:
    Not all symptoms felt around the wrist originate directly from the wrist joint.
    Peripheral nerve irritation or problems arising more proximally from the forearm, elbow or cervical region may sometimes produce pain, tingling, numbness or weakness in the wrist and hand.
    Neurological screening may therefore be required when the symptom pattern suggests nerve involvement.

Related Hand and Wrist Conditions

Trigger Finger and Wrist Drop affect hand or nerve function. They are relevant to hand and wrist rehabilitation, although neither is a primary wrist-pain diagnosis.

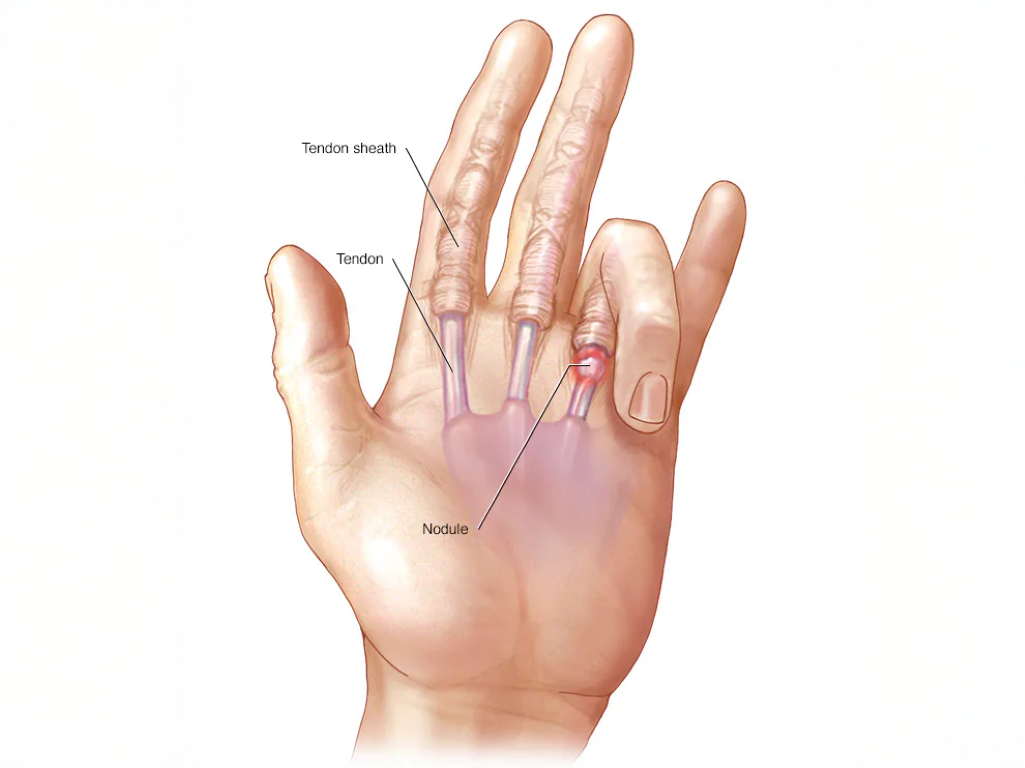
  1. Trigger Finger:
    Trigger Finger, medically known as stenosing tenosynovitis, primarily affects the flexor tendon system of a finger rather than the wrist itself.
    It can produce finger stiffness, painful clicking or popping, catching and locking of the affected finger.
    Trigger Finger is a related hand condition rather than a typical cause of wrist pain.
    Related guide: Trigger Finger: Causes, Symptoms & Physiotherapy Treatment
  2. Wrist Drop:
    Wrist Drop refers to inability or marked difficulty actively extending the wrist, usually because of radial nerve dysfunction.
    It is primarily a motor and neurological presentation. Depending on the cause, a patient may also experience altered sensation or other upper-limb symptoms, but wrist pain is not required for Wrist Drop to be present.
    Wrist Drop should therefore be assessed as a neurological problem, distinct from tendon, joint and ligament causes of wrist pain.
    Related guide: Wrist Drop: Causes, Symptoms & Physiotherapy Treatment

Risk Factors for Developing Wrist Pain

Several factors may increase stress on the wrist or contribute to specific wrist disorders:

  1. Repetitive gripping or hand activities
  2. Frequent typing, mouse use or prolonged device use
  3. Repetitive thumb movements
  4. Heavy lifting or manual work
  5. Racket sports, weight training or gymnastics
  6. Sudden increases in workload or training
  7. Previous wrist or hand injury
  8. Poor load management during repetitive activities
  9. Prolonged wrist positions during work or sleep
  10. Medical conditions that may affect joints, tendons or peripheral nerves

Having one or more risk factors does not confirm the cause of wrist pain. Symptoms should be interpreted together with the patient's history, physical examination and functional demands.

Symptoms of Wrist Pain

Symptoms vary according to the involved tissue or condition. Common complaints include:

  1. Pain on the thumb, little-finger, palm or back side of the wrist
  2. Pain during gripping or lifting
  3. Pain during wrist bending or extension
  4. Wrist stiffness or restricted range of motion
  5. Swelling or localized tenderness
  6. Reduced grip strength
  7. Difficulty typing, writing or using tools
  8. Clicking, catching or instability
  9. Tingling, burning or numbness in the hand or fingers
  10. Weakness affecting normal wrist or hand function

Wrist Pain Symptoms That Should Not Be Ignored

Some wrist symptoms require medical assessment rather than routine self-management alone.

Seek appropriate professional care if you experience:

  1. Severe wrist pain after a fall or significant trauma
  2. Visible deformity
  3. Inability to move the wrist or use the hand normally after injury
  4. Rapid or significant swelling
  5. Extensive bruising following trauma
  6. Increasing redness, warmth or fever
  7. Progressive numbness or loss of sensation
  8. Increasing hand or finger weakness
  9. Sudden inability to extend the wrist or fingers
  10. Persistent pain that continues to worsen despite reducing the aggravating activity

These symptoms do not always indicate a serious disorder, but fracture, significant ligament injury, infection or neurological dysfunction may need to be excluded before routine rehabilitation is started.

How Wrist Pain Is Diagnosed

Accurate assessment is important because tendon, nerve, ligament and joint disorders can produce similar symptoms around the wrist.

Clinical assessment may include:

  1. History of how and when symptoms started
  2. Exact location and behaviour of pain
  3. Activities that aggravate or reduce symptoms
  4. Wrist and forearm range of motion
  5. Grip and pinch strength
  6. Tendon loading assessment
  7. Ligament and joint stability testing when indicated
  8. Sensory and neurological screening
  9. Assessment of thumb and finger function
  10. Examination of the elbow or cervical region when referred symptoms are suspected
  11. Functional assessment based on work, daily activities or sport

Condition-specific clinical tests may also be selected. For example, nerve-related wrist symptoms require a different examination from thumb tendon pain or traumatic ligament injury.

Imaging is not necessary for every case of wrist pain.

When clinically indicated, further investigations may include:

  1. X-ray
  2. Musculoskeletal ultrasound
  3. MRI
  4. Nerve conduction studies or electromyography in selected neurological conditions
  5. Other investigations according to the suspected pathology

Physiotherapy Treatment for Wrist Pain

There is no single physiotherapy treatment or exercise program suitable for every wrist condition.

Rehabilitation should be based on the structure involved, severity and duration of symptoms, neurological findings, movement limitations, strength deficits and functional requirements of the patient.

  1. Education and Load Modification:
    The activities repeatedly aggravating the wrist should first be identified.
    Depending on the condition, temporary modification of gripping, lifting, typing, repetitive thumb use, sports training or weight-bearing through the wrist may help reduce excessive irritation while maintaining appropriate activity.
    Complete immobilization or complete rest is not necessary for every wrist condition.
  2. Mobility and Range-of-Motion Training:
    Pain, trauma or immobilization may reduce wrist and forearm mobility.
    Rehabilitation may address:
    1. Wrist flexion
    2. Wrist extension
    3. Radial and ulnar deviation
    4. Forearm pronation and supination
    5. Thumb and finger mobility when relevant
    The intensity of mobility work should depend on the diagnosis and tissue-healing stage.
  3. Progressive Strengthening:
    Strengthening may focus on:
    1. Wrist flexor muscles
    2. Wrist extensor muscles
    3. Forearm pronators and supinators
    4. Grip and pinch strength
    5. Thumb musculature
    6. Functional hand control
    Loading should be progressed according to symptoms and tissue capacity rather than increasing resistance too quickly.
  4. Tendon Rehabilitation:
    When wrist pain originates from tendon overload or tenosynovitis, rehabilitation may include activity modification and condition-specific progressive tendon loading.
    The program should be adapted to the affected tendon rather than applying the same exercises to every wrist-pain condition.
  5. Nerve-Related Rehabilitation:
    When Carpal Tunnel Syndrome or another peripheral nerve disorder is suspected, treatment may include appropriate activity modification, neurological monitoring, selected nerve-mobilization techniques and restoration of hand function when clinically indicated.
    Progressive or significant neurological deficits may require medical or specialist assessment.
  6. Manual Therapy:
    Manual therapy or joint mobilization may be used for selected patients with pain, stiffness or restricted movement.
    It is generally used as an adjunct to active rehabilitation rather than replacing therapeutic exercise and progressive return to function.
  7. Splinting or Support When Appropriate:
    Some conditions may benefit from temporary splinting or wrist support to reduce aggravating movement or maintain a more suitable position.
    The type and duration of support should depend on the condition and clinical assessment because unnecessary prolonged immobilization can contribute to stiffness and weakness.
  8. Functional and Activity-Specific Rehabilitation:
    As symptoms improve, rehabilitation should gradually prepare the patient for their normal activities.
    This may include:
    1. Typing and computer work
    2. Writing and fine hand activities
    3. Gripping and carrying
    4. Household tasks
    5. Manual work
    6. Gym or weight-bearing activities
    7. Racket or other upper-limb sports
  9. Electrotherapy and Other Adjuncts:
    Electrotherapy or other physical modalities may be used in selected patients when clinically indicated.
    These interventions should support, rather than replace, education, appropriate loading, therapeutic exercise and functional rehabilitation.

Why Early Assessment Matters

Persistent wrist pain may gradually reduce the way a person uses the hand. Patients may grip less firmly, avoid lifting, change typing technique or compensate excessively through the elbow and shoulder.

Neurological symptoms such as tingling or numbness may also be mistakenly treated as simple muscle or tendon pain.

Appropriate assessment helps determine whether the problem is primarily tendon-related, nerve-related, ligamentous, joint-related, post-traumatic or referred from another region.

Physiotherapy can then be directed toward the patient's actual impairments and functional goals instead of treating every wrist problem in the same way.

When Should You See a Physiotherapist for Wrist Pain?

Consider physiotherapy assessment if:

  1. Wrist pain is interfering with work or daily activities
  2. Gripping or lifting has become painful
  3. Wrist movement has become restricted
  4. Symptoms repeatedly return when activity increases
  5. Grip strength has noticeably decreased
  6. Tingling or numbness is occurring in the hand or fingers
  7. You are recovering after wrist injury, fracture immobilization or surgery
  8. Pain persists despite reasonable activity modification

If symptoms suggest fracture, major ligament injury, infection, significant nerve injury or progressive neurological weakness, appropriate medical assessment may be required before or alongside physiotherapy.

Why Asia Digital Physiotherapy Orthopedic Rehabilitation Center (ADPORC) Is a Trusted Physiotherapy Center in Dhaka

ADPORC focuses on evidence-based physiotherapy for musculoskeletal, neurological and sports-related conditions.

  1. Expert Care by Dr. Saddam Hossain, PT Structured rehabilitation under experienced clinical supervision.
  2. Condition-Specific Physiotherapy Programs Treatment plans designed according to assessment, pain stage and functional goals.
  3. Advanced Electrotherapy and Rehabilitation Equipment Modalities used only when clinically indicated.
  4. One-on-One Supervised Sessions Direct supervision supports safe and individualized rehabilitation.
  5. Accessible Location in Jatrabari, Dhaka Serving patients from Jatrabari, Dholaipar, Shonir Akhra, Doyagonj, Puran Dhaka, Keraniganj, Narayanganj and surrounding areas.

If you are looking for reliable physiotherapy for wrist pain in Dhaka, ADPORC provides structured rehabilitation based on clinical assessment, movement limitations, neurological findings and individual functional goals.

Book Your Appointment Today

Do not let persistent wrist pain, weakness or hand symptoms continue to interfere with gripping, typing, lifting or everyday activities. Appropriate assessment can help identify the likely source of symptoms and determine a suitable rehabilitation plan.

Visit ADPORC for professional physiotherapy assessment and rehabilitation for wrist pain and related hand and upper-limb conditions.

কবজির ব্যথা বা রিস্ট পেইন আপার লিম্বের একটি সাধারণ সমস্যা, যা কোনো বস্তু শক্ত করে ধরা, টাইপ করা, লেখা, জিনিস তোলা, স্মার্টফোন ব্যবহার, বোতল বা জারের ঢাকনা খোলা, এক্সারসাইজ করা কিংবা বারবার হাত ব্যবহার করতে হয় এমন কাজে অসুবিধা তৈরি করতে পারে।

কিছু রিস্ট সমস্যা বারবার গ্রিপিং, কম্পিউটার ব্যবহার, খেলাধুলা, ম্যানুয়াল কাজ বা দীর্ঘ সময় কবজিতে লোড পড়ার কারণে ধীরে ধীরে তৈরি হয়। আবার পড়ে যাওয়া, কবজি মোচড়ানো, হঠাৎ অতিরিক্ত ফোর্স বা সরাসরি আঘাতের পরও ব্যথা শুরু হতে পারে। সমস্যার ধরন অনুযায়ী ব্যথার সঙ্গে ফোলা, স্টিফনেস, দুর্বলতা, গ্রিপ স্ট্রেন্থ কমে যাওয়া, ঝিনঝিন বা অসাড়তাও থাকতে পারে।

রিস্ট একটি জটিল অঞ্চল, যা একাধিক ছোট হাড়, জয়েন্ট, লিগামেন্ট, টেনডন, টেনডন শিথ এবং নার্ভ নিয়ে গঠিত। এসব গঠন হাতকে বিভিন্ন দিকে মুভমেন্ট করতে সাহায্য করার পাশাপাশি ফোরআর্ম ও হাতের মধ্যে ফোর্স ট্রান্সফার করে। ছোট একটি অঞ্চলে অনেক গঠন কাছাকাছি অবস্থান করায় বিভিন্ন রিস্ট কন্ডিশনের উপসর্গ একে অপরের সঙ্গে মিলতে পারে।

Asia Digital Physiotherapy Orthopedic Rehabilitation Center (ADPORC)-এ রোগীর ক্লিনিক্যাল অ্যাসেসমেন্ট, পেইন প্যাটার্ন, মুভমেন্ট রেস্ট্রিকশন, গ্রিপ স্ট্রেন্থ, নিউরোলজিক্যাল ফাইন্ডিংস এবং ফাংশনাল লিমিটেশনের ভিত্তিতে রিস্ট রিহ্যাবিলিটেশন পরিকল্পনা করা হয়। প্রয়োজন অনুযায়ী অ্যাক্টিভিটি ও লোড মডিফিকেশন, থেরাপিউটিক এক্সারসাইজ, মোবিলিটি ট্রেনিং, প্রগ্রেসিভ স্ট্রেন্থেনিং, টেনডন বা নার্ভ রিহ্যাবিলিটেশন, ম্যানুয়াল থেরাপি এবং অন্যান্য ফিজিওথেরাপি ইন্টারভেনশন ব্যবহার করা হতে পারে।

কবজির ব্যথা বুঝতে গঠনভিত্তিক ধারণা

রিস্ট পেইন বলতে কবজি জয়েন্ট বা এর আশপাশের গঠন থেকে সৃষ্ট ব্যথা বা অস্বস্তিকে বোঝায়। ব্যথা কবজির বৃদ্ধাঙ্গুলির পাশে, কনিষ্ঠ আঙুলের পাশে, তালুর দিকে অথবা কবজির পেছনের দিকে অনুভূত হতে পারে। কিছু কন্ডিশনে উপসর্গ হাত, আঙুল বা ফোরআর্ম পর্যন্ত ছড়িয়ে যেতে পারে।

রিস্ট ও এর আশপাশে গুরুত্বপূর্ণ যেসব গঠন রয়েছে:

  1. ডিস্টাল ফোরআর্মের রেডিয়াস ও আলনা
  2. আটটি কার্পাল বোন
  3. রেডিওকার্পাল ও ইন্টারকার্পাল জয়েন্ট
  4. রিস্ট লিগামেন্ট
  5. ফ্লেক্সর ও এক্সটেনসর টেনডন
  6. টেনডন শিথ
  7. ট্রায়াঙ্গুলার ফাইব্রোকার্টিলেজ কমপ্লেক্স বা TFCC
  8. মিডিয়ান, আলনার ও রেডিয়াল নার্ভ
  9. কার্পাল টানেল এবং অন্যান্য সফট-টিস্যু প্যাসেজ
  10. রিস্ট, থাম্ব ও ফিঙ্গার মুভমেন্টে কাজ করা মাসল

কোন গঠন জড়িত তার ওপর ভিত্তি করে রিস্ট সমস্যায় তীক্ষ্ণ বা মৃদু ব্যথা, টেন্ডারনেস, ফোলা, স্টিফনেস, দুর্বলতা, গ্রিপ স্ট্রেন্থ কমে যাওয়া, ক্লিকিং, জ্বালাপোড়া, ঝিনঝিন বা অসাড়তা দেখা দিতে পারে।

উপসর্গের স্থান ও আচরণ সম্ভাব্য কারণ সম্পর্কে ধারণা দিতে পারে, তবে শুধু এগুলোর ওপর ভিত্তি করে নিশ্চিত ডায়াগনসিস করা যায় না।

কবজির ব্যথার সাধারণ স্থান এবং এগুলো কী নির্দেশ করতে পারে

রিস্টের কোন অংশে ব্যথা হচ্ছে, তা কোন গঠন আরও বিস্তারিতভাবে অ্যাসেসমেন্ট করা প্রয়োজন সে সম্পর্কে গুরুত্বপূর্ণ ধারণা দিতে পারে।

  1. বৃদ্ধাঙ্গুলির পাশের কবজিতে ব্যথা:
    রিস্টের রেডিয়াল বা বৃদ্ধাঙ্গুলির পাশের ব্যথা সাধারণত ডি কুয়েরভেইনস টেনোসাইনোভাইটিস-এর সঙ্গে সম্পর্কিত হতে পারে।
    গ্রিপিং, শিশুকে কোলে তোলা, কোনো কিছু ঘোরানো, জারের ঢাকনা খোলা, স্মার্টফোন ব্যবহার বা বারবার বৃদ্ধাঙ্গুলি মুভমেন্টের সময় ব্যথা বাড়তে পারে।
    ডি কুয়েরভেইনস টেনোসাইনোভাইটিসে সাধারণত APL এবং EPB টেনডনের অঞ্চল জড়িত থাকে এবং গ্রিপিং, টুইস্টিং ও লিফটিংয়ের সময় ব্যথা বেড়ে যেতে পারে।
  2. তালুর দিকের কবজিতে ব্যথা, ঝিনঝিন বা অসাড়তা:
    রিস্টের পালমার বা তালুর দিকে ব্যথা, জ্বালাপোড়া, ঝিনঝিন বা অসাড়তা থাকলে কার্পাল টানেল সিনড্রোম বিবেচনা করা যেতে পারে, বিশেষ করে যখন উপসর্গ বৃদ্ধাঙ্গুলি, ইনডেক্স ও মিডল ফিঙ্গারে অনুভূত হয়।
    রাতে, দীর্ঘ সময় টাইপিং, ড্রাইভিং, ফোন ধরে রাখা বা দীর্ঘ সময় একই ধরনের হাতের কাজ করলে উপসর্গ বাড়তে পারে।
    কার্পাল টানেল সিনড্রোমে রিস্টের কার্পাল টানেলের ভেতরে মিডিয়ান নার্ভ কমপ্রেসড হয়।
  3. কনিষ্ঠ আঙুলের পাশের কবজিতে ব্যথা:
    রিস্টের আলনার বা কনিষ্ঠ আঙুলের পাশের ব্যথা TFCC, এক্সটেনসর কার্পি আলনারিস টেনডন অথবা অন্যান্য আলনার-সাইডেড রিস্ট স্ট্রাকচারের সঙ্গে সম্পর্কিত হতে পারে।
    গ্রিপিং, ফোরআর্ম রোটেশন, হাত দিয়ে ধাক্কা দেওয়া বা কবজির ওপর ওয়েট-বেয়ারিংয়ের সময় ব্যথা বাড়তে পারে।
  4. কবজির পেছনের দিকে ব্যথা:
    ডরসাল রিস্ট পেইন এক্সটেনসর টেনডন সমস্যা, লিগামেন্ট ইনজুরি, গ্যাংলিয়ন সিস্ট অথবা জয়েন্ট-সম্পর্কিত কন্ডিশনের কারণে হতে পারে।
    বিশেষ করে রিস্ট এক্সটেনশন, পুশ-আপ, ওয়েট ট্রেনিং বা দীর্ঘ সময় হাতের ওপর ভর দেওয়ার সময় ব্যথা বেশি অনুভূত হতে পারে।
  5. পড়ে যাওয়া বা হঠাৎ ইনজুরির পর কবজির ব্যথা:
    হাতের ওপর ভর দিয়ে পড়ে যাওয়া, কবজি মোচড়ানো বা সরাসরি আঘাতের পর হঠাৎ ব্যথা শুরু হলে রিস্ট স্প্রেইন, লিগামেন্ট ইনজুরি বা ফ্র্যাকচার হতে পারে।
    উল্লেখযোগ্য ফোলা, ব্রুইজিং, ডিফর্মিটি বা হাত ব্যবহার করতে অসুবিধা হলে যথাযথ মেডিক্যাল অ্যাসেসমেন্ট প্রয়োজন।
  6. ক্লিকিং বা ইনস্ট্যাবিলিটিসহ কবজির ব্যথা:
    ক্লিকিং, ক্যাচিং, রোটেশনের সময় ব্যথা অথবা কবজি অস্থিতিশীল মনে হওয়া লিগামেন্ট বা TFCC-সম্পর্কিত ইনজুরিতে দেখা দিতে পারে।
    একাধিক রিস্ট স্ট্রাকচার একই ধরনের মেকানিক্যাল উপসর্গ তৈরি করতে পারে, তাই ক্লিনিক্যাল অ্যাসেসমেন্ট গুরুত্বপূর্ণ।
  7. কবজির দুর্বলতা বা হাত উপরে তুলতে অসুবিধা:
    রিস্ট এক্সটেনশনে উল্লেখযোগ্য দুর্বলতা, বিশেষ করে সক্রিয়ভাবে কবজি ও আঙুল উপরের দিকে তুলতে না পারা, সাধারণ রিস্ট পেইনের চেয়ে নিউরোলজিক্যাল সমস্যার ইঙ্গিত দিতে পারে।
    এর একটি উদাহরণ হলো রিস্ট ড্রপ, যা সাধারণত রেডিয়াল নার্ভ ডিসফাংশনের সঙ্গে সম্পর্কিত।
    রিস্ট ড্রপের সঙ্গে ব্যথা থাকতেও পারে, আবার নাও থাকতে পারে। তাই একে সাধারণ কবজির ব্যথা না ধরে নিউরোলজিক্যাল ও ফাংশনাল সমস্যা হিসেবে মূল্যায়ন করা উচিত।

কবজির ব্যথার সাধারণ কারণসমূহ

রিস্ট পেইন টেনডন, টেনডন শিথ, নার্ভ, লিগামেন্ট, কার্টিলেজ, হাড় বা জয়েন্ট থেকে তৈরি হতে পারে। নিচে কয়েকটি গুরুত্বপূর্ণ কারণ আলোচনা করা হলো।

  1. ডি কুয়েরভেইনস টেনোসাইনোভাইটিস:
    ডি কুয়েরভেইনস টেনোসাইনোভাইটিস রিস্টের বৃদ্ধাঙ্গুলির পাশ দিয়ে যাওয়া টেনডনকে প্রভাবিত করে, বিশেষ করে অ্যাবডাক্টর পলিসিস লংগাস এবং এক্সটেনসর পলিসিস ব্রেভিস টেনডন।
    বারবার বৃদ্ধাঙ্গুলি ও কবজি ব্যবহার করার কারণে টেনডন শিথ ইরিটেটেড হতে পারে এবং টেনডনের স্বাভাবিক গ্লাইডিং ব্যথাযুক্ত হয়ে যায়।
    রোগীদের সাধারণত বৃদ্ধাঙ্গুলির পাশের কবজিতে ব্যথা, ফোলা, গ্রিপ স্ট্রেন্থ কমে যাওয়া এবং গ্রিপিং, টুইস্টিং বা লিফটিংয়ের সময় অস্বস্তি হয়।
    সম্পর্কিত গাইড: ডি কুয়েরভেইনস টেনোসাইনোভাইটিস: কারণ, উপসর্গ ও ফিজিওথেরাপি চিকিৎসা
  2. কার্পাল টানেল সিনড্রোম:
    কার্পাল টানেল সিনড্রোম বা CTS হলো একটি নার্ভ কমপ্রেশন কন্ডিশন, যেখানে মিডিয়ান নার্ভ রিস্টের কার্পাল টানেলের মধ্য দিয়ে যাওয়ার সময় কমপ্রেসড হয়।
    এতে অসাড়তা, ঝিনঝিন, জ্বালাপোড়া, রাতে উপসর্গ বেড়ে যাওয়া, গ্রিপ স্ট্রেন্থ কমে যাওয়া অথবা সূক্ষ্ম হাতের কাজ করতে অসুবিধা হতে পারে। কিছু রোগীর হাত থেকে জিনিস বারবার পড়ে যাওয়ার সমস্যাও দেখা দিতে পারে।
    সম্পর্কিত গাইড: কার্পাল টানেল সিনড্রোম (CTS): কারণ, উপসর্গ ও ফিজিওথেরাপি চিকিৎসা
  3. রিস্ট স্প্রেইন ও লিগামেন্ট ইনজুরি:
    রিস্টের এক বা একাধিক লিগামেন্ট অতিরিক্ত স্ট্রেচড বা ইনজুরড হলে রিস্ট স্প্রেইন হতে পারে।
    হাতের ওপর ভর দিয়ে পড়ে যাওয়া, হঠাৎ কবজি মোচড়ানো, স্পোর্টস ইনজুরি অথবা অন্য কোনো ট্রমার কারণে এটি হতে পারে।
    ব্যথা, ফোলা, টেন্ডারনেস, মুভমেন্ট কমে যাওয়া এবং গ্রিপিং বা হাতের ওপর ভর দিতে অসুবিধা হতে পারে।
    রিস্ট লিগামেন্ট ইনজুরির তীব্রতা ভিন্ন হতে পারে। উল্লেখযোগ্য ট্রমাটিক উপসর্গ থাকলে ফ্র্যাকচার বা বড় ধরনের ইনস্ট্যাবিলিটি বাদ দেওয়ার জন্য অ্যাসেসমেন্ট প্রয়োজন।
  4. রিস্ট টেন্ডিনোপ্যাথি ও টেনোসাইনোভাইটিস:
    হাত ও আঙুলের মুভমেন্ট নিয়ন্ত্রণকারী বেশ কয়েকটি টেনডন রিস্টের মধ্য দিয়ে যায়।
    বারবার গ্রিপিং, লিফটিং, র‍্যাকেট স্পোর্টস, জিম ট্রেনিং, ম্যানুয়াল কাজ বা হঠাৎ অ্যাক্টিভিটি বাড়ালে এসব টেনডনের ওপর অতিরিক্ত লোড পড়তে পারে।
    রিস্ট মুভমেন্টের সময় নির্দিষ্ট জায়গায় ব্যথা, টেনডনের ওপর টেন্ডারনেস এবং গ্রিপিং বা রেজিস্টেড মুভমেন্টে অস্বস্তি দেখা দিতে পারে।
  5. ট্রায়াঙ্গুলার ফাইব্রোকার্টিলেজ কমপ্লেক্স বা TFCC ইনজুরি:
    TFCC রিস্টের আলনার পাশে গুরুত্বপূর্ণ একটি স্ট্যাবিলাইজিং স্ট্রাকচার।
    পড়ে যাওয়া, জোরে ফোরআর্ম রোটেশন অথবা বারবার লোড পড়ার কারণে এটি ইনজুরড হতে পারে।
    কনিষ্ঠ আঙুলের পাশের রিস্ট পেইন, ক্লিকিং, দুর্বলতা অথবা ফোরআর্ম ঘোরানো, গ্রিপিং বা হাত দিয়ে চাপ দেওয়ার সময় ব্যথা হতে পারে।
  6. গ্যাংলিয়ন সিস্ট:
    গ্যাংলিয়ন সিস্ট হলো ফ্লুইড-ফিল্ড একটি লাম্প, যা সাধারণত রিস্ট বা হাতের আশপাশে দেখা যায়।
    কিছু গ্যাংলিয়ন সিস্টে কোনো উপসর্গ থাকে না। আবার কিছু ক্ষেত্রে লোকালাইজড অস্বস্তি, চাপ, মুভমেন্ট রেস্ট্রিকশন বা রিস্টে লোড দেওয়ার সময় ব্যথা হতে পারে।
    রিস্টের কাছে নতুন কোনো লাম্প বা সময়ের সঙ্গে পরিবর্তিত হওয়া লাম্পকে পরীক্ষা ছাড়া গ্যাংলিয়ন সিস্ট ধরে নেওয়া উচিত নয়।
  7. রিস্ট অস্টিওআর্থ্রাইটিস ও অন্যান্য জয়েন্ট ডিসঅর্ডার:
    ডিজেনারেটিভ বা ইনফ্ল্যামেটরি জয়েন্ট কন্ডিশনে রিস্টের গভীরে ব্যথা, স্টিফনেস, ফোলা এবং রেঞ্জ অব মোশন কমে যেতে পারে।
    আগের ফ্র্যাকচার বা উল্লেখযোগ্য রিস্ট ইনজুরির পর পরবর্তীতে পোস্ট-ট্রমাটিক জয়েন্ট পরিবর্তনও হতে পারে।
  8. রিস্ট ফ্র্যাকচার ও পোস্ট-ট্রমাটিক পেইন:
    পড়ে যাওয়া বা উল্লেখযোগ্য ট্রমার কারণে ডিস্টাল রেডিয়াস অথবা কার্পাল বোনে ফ্র্যাকচার হতে পারে।
    ফ্র্যাকচার হিল হওয়ার পরও কিছু রোগীর স্টিফনেস, দুর্বলতা, গ্রিপ স্ট্রেন্থ কমে যাওয়া এবং স্বাভাবিকভাবে হাত ব্যবহার করতে অসুবিধা থাকতে পারে, যেখানে রিহ্যাবিলিটেশন প্রয়োজন হতে পারে।
    ইনজুরির পর দীর্ঘস্থায়ী ব্যথাকে যথাযথ অ্যাসেসমেন্ট ছাড়া সাধারণ স্প্রেইন ধরে নেওয়া উচিত নয়।
  9. নার্ভ-সম্পর্কিত বা রেফার্ড রিস্ট পেইন:
    রিস্টের আশপাশে অনুভূত সব উপসর্গই রিস্ট জয়েন্ট থেকে আসে না।
    পেরিফেরাল নার্ভ ইরিটেশন অথবা ফোরআর্ম, এলবো বা সার্ভিক্যাল রিজিয়নের আরও উপরের কোনো সমস্যা রিস্ট ও হাতে ব্যথা, ঝিনঝিন, অসাড়তা বা দুর্বলতা তৈরি করতে পারে।
    তাই উপসর্গের প্যাটার্ন নার্ভ ইনভলভমেন্টের ইঙ্গিত দিলে নিউরোলজিক্যাল স্ক্রিনিং করা প্রয়োজন হতে পারে।

হাত ও কবজির সম্পর্কিত অন্যান্য কন্ডিশন

ট্রিগার ফিঙ্গার এবং রিস্ট ড্রপ হাতের ফাংশন ও পুনর্বাসনের সঙ্গে সম্পর্কিত হলেও এগুলো সাধারণ কবজির ব্যথার প্রধান কারণ নয়।

  1. ট্রিগার ফিঙ্গার:
    ট্রিগার ফিঙ্গার, মেডিক্যালি যাকে স্টেনোসিং টেনোসাইনোভাইটিস বলা হয়, মূলত একটি আঙুলের ফ্লেক্সর টেনডন মেকানিজমকে প্রভাবিত করে, রিস্টকে নয়।
    এতে ফিঙ্গার স্টিফনেস, ব্যথাযুক্ত ক্লিকিং বা পপিং, ক্যাচিং এবং আঙুল বাঁকা অবস্থায় লক হয়ে যাওয়ার মতো সমস্যা হতে পারে।
    ট্রিগার ফিঙ্গার হাতের একটি সম্পর্কিত সমস্যা, তবে এটিকে সাধারণ কবজির ব্যথার কারণ হিসেবে বিবেচনা করা উচিত নয়।
    সম্পর্কিত গাইড: ট্রিগার ফিঙ্গার: কারণ, উপসর্গ ও ফিজিওথেরাপি চিকিৎসা
  2. রিস্ট ড্রপ:
    রিস্ট ড্রপ বলতে সক্রিয়ভাবে রিস্ট এক্সটেনশন করতে না পারা বা উল্লেখযোগ্য অসুবিধাকে বোঝায়, যা সাধারণত রেডিয়াল নার্ভ ডিসফাংশনের কারণে হয়।
    এটি প্রধানত একটি মোটর ও নিউরোলজিক্যাল প্রেজেন্টেশন। মূল সমস্যার ওপর ভিত্তি করে সেনসেশন পরিবর্তন বা অন্যান্য আপার লিম্ব উপসর্গ থাকতে পারে, তবে রিস্ট ড্রপ হওয়ার জন্য কবজিতে ব্যথা থাকা আবশ্যক নয়।
    তাই রিস্ট ড্রপকে টেনডন, জয়েন্ট বা লিগামেন্ট-সম্পর্কিত কবজির ব্যথা থেকে আলাদা একটি নিউরোলজিক্যাল সমস্যা হিসেবে মূল্যায়ন করা উচিত।
    সম্পর্কিত গাইড: রিস্ট ড্রপ: কারণ, উপসর্গ ও ফিজিওথেরাপি চিকিৎসা

কবজির ব্যথার ঝুঁকির কারণসমূহ

কিছু বিষয় রিস্টের ওপর অতিরিক্ত চাপ সৃষ্টি করতে পারে অথবা নির্দিষ্ট কিছু কন্ডিশনে ভূমিকা রাখতে পারে:

  1. বারবার গ্রিপিং বা হাতের পুনরাবৃত্তিমূলক কাজ
  2. ঘন ঘন টাইপিং, মাউস ব্যবহার বা দীর্ঘ সময় ডিভাইস ব্যবহার
  3. বারবার বৃদ্ধাঙ্গুলি মুভমেন্ট
  4. ভারী জিনিস তোলা বা ম্যানুয়াল কাজ
  5. র‍্যাকেট স্পোর্টস, ওয়েট ট্রেনিং বা জিমন্যাস্টিকস
  6. হঠাৎ কাজ বা ট্রেনিংয়ের পরিমাণ বাড়ানো
  7. আগের রিস্ট বা হাতের ইনজুরি
  8. রিপিটেড অ্যাক্টিভিটিতে ভুল লোড ম্যানেজমেন্ট
  9. কাজ বা ঘুমের সময় দীর্ঘক্ষণ একই রিস্ট পজিশনে থাকা
  10. জয়েন্ট, টেনডন বা পেরিফেরাল নার্ভকে প্রভাবিত করতে পারে এমন মেডিক্যাল কন্ডিশন

এক বা একাধিক রিস্ক ফ্যাক্টর থাকলেই রিস্ট পেইনের কারণ নিশ্চিত হয়ে যায় না। রোগীর ইতিহাস, ফিজিক্যাল এক্সামিনেশন ও ফাংশনাল ডিমান্ডের সঙ্গে মিলিয়ে উপসর্গ মূল্যায়ন করা প্রয়োজন।

কবজির ব্যথার সাধারণ উপসর্গ

কোন টিস্যু বা কন্ডিশন জড়িত তার ওপর ভিত্তি করে উপসর্গ ভিন্ন হতে পারে। সাধারণ উপসর্গগুলোর মধ্যে রয়েছে:

  1. বৃদ্ধাঙ্গুলির পাশ, কনিষ্ঠ আঙুলের পাশ, তালুর দিক অথবা রিস্টের পেছনে ব্যথা
  2. গ্রিপিং বা লিফটিংয়ের সময় ব্যথা
  3. রিস্ট বাঁকানো বা এক্সটেনশনের সময় ব্যথা
  4. রিস্ট স্টিফনেস বা রেঞ্জ অব মোশন কমে যাওয়া
  5. ফোলা বা নির্দিষ্ট জায়গায় টেন্ডারনেস
  6. গ্রিপ স্ট্রেন্থ কমে যাওয়া
  7. টাইপিং, লেখা বা টুল ব্যবহার করতে অসুবিধা
  8. ক্লিকিং, ক্যাচিং বা ইনস্ট্যাবিলিটি
  9. হাত বা আঙুলে ঝিনঝিন, জ্বালাপোড়া বা অসাড়তা
  10. রিস্ট ও হাতের স্বাভাবিক ফাংশনে প্রভাব ফেলে এমন দুর্বলতা

কবজির ব্যথার যেসব উপসর্গ অবহেলা করা উচিত নয়

কিছু রিস্ট উপসর্গ সাধারণ সেলফ-ম্যানেজমেন্টের পরিবর্তে মেডিক্যাল অ্যাসেসমেন্টের প্রয়োজন হতে পারে।

নিচের কোনো উপসর্গ থাকলে যথাযথ প্রফেশনাল অ্যাসেসমেন্ট নিন:

  1. পড়ে যাওয়া বা বড় ধরনের ট্রমার পর তীব্র রিস্ট পেইন
  2. দৃশ্যমান ডিফর্মিটি
  3. ইনজুরির পর রিস্ট নাড়াতে বা স্বাভাবিকভাবে হাত ব্যবহার করতে না পারা
  4. দ্রুত বা উল্লেখযোগ্য ফোলা
  5. ট্রমার পর ব্যাপক ব্রুইজিং
  6. ক্রমশ বাড়তে থাকা লালভাব, গরম অনুভূতি বা জ্বর
  7. অসাড়তা বা সেনসেশন কমে যাওয়া ক্রমশ বাড়তে থাকা
  8. হাত বা আঙুলের দুর্বলতা বাড়তে থাকা
  9. হঠাৎ রিস্ট বা আঙুল এক্সটেনশন করতে না পারা
  10. অ্যাক্টিভিটি কমানোর পরও ব্যথা ক্রমশ বেড়ে যাওয়া

এসব উপসর্গ সবসময় গুরুতর কোনো সমস্যা নির্দেশ করে না। তবে সাধারণ রিহ্যাবিলিটেশন শুরু করার আগে ফ্র্যাকচার, উল্লেখযোগ্য লিগামেন্ট ইনজুরি, ইনফেকশন বা নিউরোলজিক্যাল ডিসফাংশন বাদ দেওয়া প্রয়োজন হতে পারে।

কবজির ব্যথা কীভাবে নির্ণয় করা হয়

টেনডন, নার্ভ, লিগামেন্ট ও জয়েন্টের বিভিন্ন সমস্যা রিস্টের আশপাশে কাছাকাছি ধরনের উপসর্গ তৈরি করতে পারে। তাই সঠিক অ্যাসেসমেন্ট গুরুত্বপূর্ণ।

ক্লিনিক্যাল অ্যাসেসমেন্টের মধ্যে থাকতে পারে:

  1. কখন ও কীভাবে উপসর্গ শুরু হয়েছে তার ইতিহাস
  2. ব্যথার নির্দিষ্ট অবস্থান ও আচরণ
  3. কোন অ্যাক্টিভিটিতে উপসর্গ বাড়ে বা কমে
  4. রিস্ট ও ফোরআর্ম রেঞ্জ অব মোশন
  5. গ্রিপ ও পিঞ্চ স্ট্রেন্থ
  6. টেনডন লোডিং অ্যাসেসমেন্ট
  7. প্রয়োজন অনুযায়ী লিগামেন্ট ও জয়েন্ট স্ট্যাবিলিটি টেস্ট
  8. সেনসরি ও নিউরোলজিক্যাল স্ক্রিনিং
  9. থাম্ব ও ফিঙ্গার ফাংশন অ্যাসেসমেন্ট
  10. রেফার্ড উপসর্গের সন্দেহ থাকলে এলবো বা সার্ভিক্যাল রিজিয়ন পরীক্ষা
  11. কাজ, দৈনন্দিন অ্যাক্টিভিটি বা স্পোর্টসভিত্তিক ফাংশনাল অ্যাসেসমেন্ট

সম্ভাব্য কন্ডিশন অনুযায়ী নির্দিষ্ট ক্লিনিক্যাল টেস্ট নির্বাচন করা হয়। যেমন নার্ভ-সম্পর্কিত রিস্ট উপসর্গ, বৃদ্ধাঙ্গুলির পাশের টেনডন পেইন এবং ট্রমাটিক লিগামেন্ট ইনজুরির ক্ষেত্রে একই ধরনের অ্যাসেসমেন্ট যথেষ্ট নয়।

প্রতিটি রিস্ট পেইনের জন্য ইমেজিং প্রয়োজন হয় না।

ক্লিনিক্যালি প্রয়োজন হলে নিচের ইনভেস্টিগেশনগুলো করা হতে পারে:

  1. এক্স-রে
  2. মাসকুলোস্কেলেটাল আল্ট্রাসাউন্ড
  3. এমআরআই
  4. নির্বাচিত নিউরোলজিক্যাল কন্ডিশনে নার্ভ কনডাকশন স্টাডি বা ইলেকট্রোমায়োগ্রাফি
  5. সম্ভাব্য প্যাথোলজি অনুযায়ী অন্যান্য ইনভেস্টিগেশন

কবজির ব্যথায় ফিজিওথেরাপি চিকিৎসা

সব ধরনের রিস্ট কন্ডিশনের জন্য একটি নির্দিষ্ট ফিজিওথেরাপি ট্রিটমেন্ট বা এক্সারসাইজ প্রোগ্রাম উপযুক্ত নয়।

রিহ্যাবিলিটেশন নির্ভর করে কোন স্ট্রাকচার জড়িত, উপসর্গের তীব্রতা ও সময়কাল, নিউরোলজিক্যাল ফাইন্ডিংস, মুভমেন্ট লিমিটেশন, স্ট্রেন্থ ডেফিসিট এবং রোগীর ফাংশনাল চাহিদার ওপর।

  1. এডুকেশন ও লোড মডিফিকেশন:
    প্রথমে কোন অ্যাক্টিভিটিগুলো বারবার রিস্টের উপসর্গ বাড়াচ্ছে তা শনাক্ত করা গুরুত্বপূর্ণ।
    কন্ডিশন অনুযায়ী সাময়িকভাবে গ্রিপিং, লিফটিং, টাইপিং, বারবার বৃদ্ধাঙ্গুলি ব্যবহার, স্পোর্টস ট্রেনিং অথবা রিস্টের ওপর ওয়েট-বেয়ারিং মডিফাই করা যেতে পারে।
    তবে সব ধরনের রিস্ট কন্ডিশনে সম্পূর্ণ ইমোবিলাইজেশন বা সম্পূর্ণ বিশ্রাম প্রয়োজন হয় না।
  2. মোবিলিটি ও রেঞ্জ-অব-মোশন ট্রেনিং:
    ব্যথা, ট্রমা বা ইমোবিলাইজেশনের কারণে রিস্ট ও ফোরআর্মের মুভমেন্ট কমে যেতে পারে।
    রিহ্যাবিলিটেশনে কাজ করা হতে পারে:
    1. রিস্ট ফ্লেক্সন
    2. রিস্ট এক্সটেনশন
    3. রেডিয়াল ও আলনার ডেভিয়েশন
    4. ফোরআর্ম প্রোনেশন ও সুপিনেশন
    5. প্রয়োজন অনুযায়ী থাম্ব ও ফিঙ্গার মোবিলিটি
    মোবিলিটি ট্রেনিংয়ের ইনটেনসিটি ডায়াগনসিস এবং টিস্যু হিলিং স্টেজ অনুযায়ী নির্ধারণ করা উচিত।
  3. প্রগ্রেসিভ স্ট্রেন্থেনিং:
    স্ট্রেন্থেনিং প্রোগ্রামে গুরুত্ব দেওয়া হতে পারে:
    1. রিস্ট ফ্লেক্সর মাসল
    2. রিস্ট এক্সটেনসর মাসল
    3. ফোরআর্ম প্রোনেটর ও সুপিনেটর
    4. গ্রিপ ও পিঞ্চ স্ট্রেন্থ
    5. থাম্ব মাসকুলেচার
    6. ফাংশনাল হ্যান্ড কন্ট্রোল
    উপসর্গ ও টিস্যুর লোড নেওয়ার ক্ষমতা অনুযায়ী ধীরে ধীরে রেজিস্ট্যান্স বাড়ানো উচিত।
  4. টেনডন রিহ্যাবিলিটেশন:
    টেনডন ওভারলোড বা টেনোসাইনোভাইটিস থেকে রিস্ট পেইন হলে অ্যাক্টিভিটি মডিফিকেশন এবং কন্ডিশন-স্পেসিফিক প্রগ্রেসিভ টেনডন লোডিং ব্যবহার করা হতে পারে।
    কোন টেনডন জড়িত তার ওপর ভিত্তি করে প্রোগ্রাম পরিবর্তন করা উচিত। সব ধরনের রিস্ট পেইনের জন্য একই এক্সারসাইজ প্রয়োগ করা উপযুক্ত নয়।
  5. নার্ভ-সম্পর্কিত রিহ্যাবিলিটেশন:
    কার্পাল টানেল সিনড্রোম বা অন্য কোনো পেরিফেরাল নার্ভ কন্ডিশনের সন্দেহ থাকলে প্রয়োজন অনুযায়ী অ্যাক্টিভিটি মডিফিকেশন, নিউরোলজিক্যাল মনিটরিং, নির্বাচিত নার্ভ মোবিলাইজেশন টেকনিক এবং হ্যান্ড ফাংশন পুনরুদ্ধারের ওপর কাজ করা হতে পারে।
    প্রগ্রেসিভ বা উল্লেখযোগ্য নিউরোলজিক্যাল ডেফিসিট থাকলে মেডিক্যাল বা স্পেশালিস্ট অ্যাসেসমেন্ট প্রয়োজন হতে পারে।
  6. ম্যানুয়াল থেরাপি:
    নির্বাচিত রোগীর ক্ষেত্রে ব্যথা, স্টিফনেস বা মুভমেন্ট রেস্ট্রিকশন কমাতে ম্যানুয়াল থেরাপি বা জয়েন্ট মোবিলাইজেশন ব্যবহার করা যেতে পারে।
    এটি সাধারণত অ্যাক্টিভ রিহ্যাবিলিটেশনের সহায়ক হিসেবে ব্যবহৃত হয়, থেরাপিউটিক এক্সারসাইজ এবং প্রগ্রেসিভ রিটার্ন টু ফাংশনের বিকল্প হিসেবে নয়।
  7. প্রয়োজন অনুযায়ী স্প্লিন্টিং বা সাপোর্ট:
    কিছু কন্ডিশনে সাময়িক স্প্লিন্ট বা রিস্ট সাপোর্ট উপকারী হতে পারে, বিশেষ করে নির্দিষ্ট মুভমেন্ট কমানো বা কবজিকে তুলনামূলক উপযুক্ত পজিশনে রাখার জন্য।
    কোন ধরনের সাপোর্ট কতদিন ব্যবহার করা হবে তা কন্ডিশন ও ক্লিনিক্যাল অ্যাসেসমেন্ট অনুযায়ী নির্ধারণ করা উচিত। অপ্রয়োজনীয়ভাবে দীর্ঘদিন ইমোবিলাইজেশন করলে স্টিফনেস ও দুর্বলতা বাড়তে পারে।
  8. ফাংশনাল ও অ্যাক্টিভিটি-স্পেসিফিক রিহ্যাবিলিটেশন:
    উপসর্গ উন্নত হলে ধীরে ধীরে রোগীর স্বাভাবিক কাজের জন্য রিস্ট ও হাতকে প্রস্তুত করা উচিত।
    এর মধ্যে থাকতে পারে:
    1. টাইপিং ও কম্পিউটার কাজ
    2. লেখা ও সূক্ষ্ম হাতের কাজ
    3. গ্রিপিং ও ক্যারিং
    4. ঘরের দৈনন্দিন কাজ
    5. ম্যানুয়াল কাজ
    6. জিম বা ওয়েট-বেয়ারিং অ্যাক্টিভিটি
    7. র‍্যাকেট বা অন্যান্য আপার লিম্ব স্পোর্টস
  9. ইলেকট্রোথেরাপি ও অন্যান্য অ্যাডজাঙ্কট:
    ক্লিনিক্যালি প্রয়োজন হলে নির্বাচিত রোগীর ক্ষেত্রে ইলেকট্রোথেরাপি বা অন্যান্য ফিজিক্যাল মডালিটি ব্যবহার করা যেতে পারে।
    এসব ইন্টারভেনশন এডুকেশন, উপযুক্ত লোডিং, থেরাপিউটিক এক্সারসাইজ এবং ফাংশনাল রিহ্যাবিলিটেশনকে সহায়তা করবে – এগুলোর বিকল্প হিসেবে ব্যবহার করা উচিত নয়।

কেন সময়মতো অ্যাসেসমেন্ট গুরুত্বপূর্ণ

দীর্ঘদিন রিস্ট পেইন থাকলে একজন ব্যক্তি ধীরে ধীরে হাতের স্বাভাবিক ব্যবহার কমিয়ে দিতে পারেন। গ্রিপ কম শক্ত করে ধরা, ভারী কিছু না তোলা, টাইপিংয়ের ধরন পরিবর্তন করা অথবা এলবো ও শোল্ডার দিয়ে অতিরিক্ত কম্পেনসেশন শুরু হতে পারে।

ঝিনঝিন বা অসাড়তার মতো নিউরোলজিক্যাল উপসর্গও অনেক সময় সাধারণ মাসল বা টেনডন পেইন হিসেবে ভুলভাবে ধরে নেওয়া হয়।

যথাযথ অ্যাসেসমেন্টের মাধ্যমে সমস্যাটি প্রধানত টেনডন, নার্ভ, লিগামেন্ট, জয়েন্ট, পোস্ট-ট্রমাটিক পরিবর্তন নাকি অন্য অঞ্চল থেকে রেফার্ড উপসর্গের কারণে হচ্ছে তা শনাক্ত করা যায়।

এরপর রোগীর প্রকৃত সমস্যা ও ফাংশনাল গোল অনুযায়ী ফিজিওথেরাপি পরিকল্পনা করা সম্ভব হয়, সব ধরনের রিস্ট সমস্যাকে একইভাবে চিকিৎসা করার পরিবর্তে।

কবজির ব্যথায় কখন ফিজিওথেরাপিস্টের কাছে যাবেন?

নিচের পরিস্থিতিতে ফিজিওথেরাপি অ্যাসেসমেন্ট বিবেচনা করতে পারেন:

  1. রিস্ট পেইন কাজ বা দৈনন্দিন কার্যকলাপে বাধা সৃষ্টি করলে
  2. গ্রিপিং বা লিফটিং ব্যথাযুক্ত হয়ে গেলে
  3. রিস্ট মুভমেন্ট কমে গেলে
  4. অ্যাক্টিভিটি বাড়ালেই উপসর্গ বারবার ফিরে এলে
  5. গ্রিপ স্ট্রেন্থ উল্লেখযোগ্যভাবে কমে গেলে
  6. হাত বা আঙুলে ঝিনঝিন বা অসাড়তা হলে
  7. রিস্ট ইনজুরি, ফ্র্যাকচার ইমোবিলাইজেশন বা সার্জারির পর রিহ্যাবিলিটেশন প্রয়োজন হলে
  8. যথাযথ অ্যাক্টিভিটি মডিফিকেশনের পরও ব্যথা থেকে গেলে

যদি উপসর্গ দেখে ফ্র্যাকচার, বড় ধরনের লিগামেন্ট ইনজুরি, ইনফেকশন, উল্লেখযোগ্য নার্ভ ইনজুরি বা ক্রমশ বাড়তে থাকা নিউরোলজিক্যাল দুর্বলতার সন্দেহ হয়, তাহলে ফিজিওথেরাপির আগে বা পাশাপাশি যথাযথ মেডিক্যাল অ্যাসেসমেন্ট প্রয়োজন হতে পারে।

কেন Asia Digital Physiotherapy Orthopedic Rehabilitation Center (ADPORC) ঢাকায় একটি বিশ্বস্ত ফিজিওথেরাপি সেন্টার

ADPORC-এ মাসকুলোস্কেলেটাল, নিউরোলজিক্যাল এবং স্পোর্টস-সম্পর্কিত সমস্যার জন্য এভিডেন্স-বেইজড ফিজিওথেরাপিতে গুরুত্ব দেওয়া হয়।

  1. ডা. সাদ্দাম হোসেন, পিটি-এর তত্ত্বাবধানে চিকিৎসা অভিজ্ঞ ক্লিনিক্যাল তত্ত্বাবধানে স্ট্রাকচারড রিহ্যাবিলিটেশন।
  2. কন্ডিশন-স্পেসিফিক ফিজিওথেরাপি প্রোগ্রাম রোগীর অ্যাসেসমেন্ট, ব্যথার পর্যায় এবং ফাংশনাল গোল অনুযায়ী ট্রিটমেন্ট প্ল্যান তৈরি করা হয়।
  3. অ্যাডভান্সড ইলেকট্রোথেরাপি ও রিহ্যাবিলিটেশন ইকুইপমেন্ট ক্লিনিক্যালি প্রয়োজন অনুযায়ী মডালিটি ব্যবহার করা হয়।
  4. ওয়ান-অন-ওয়ান সুপারভাইজড সেশন সরাসরি তত্ত্বাবধানের মাধ্যমে নিরাপদ ও ব্যক্তিভিত্তিক রিহ্যাবিলিটেশন প্রদান করা হয়।
  5. সহজ ও সুবিধাজনক লোকেশন, যাত্রাবাড়ী, ঢাকা যাত্রাবাড়ী, ধোলাইপাড়, শনির আখড়া, দয়াগঞ্জ, পুরান ঢাকা, কেরানীগঞ্জ, নারায়ণগঞ্জ এবং আশপাশের এলাকার রোগীরা সেবা নিতে পারেন।

আপনি যদি ঢাকায় কবজির ব্যথার জন্য নির্ভরযোগ্য ফিজিওথেরাপি খুঁজে থাকেন, তাহলে ADPORC রোগীর ক্লিনিক্যাল অ্যাসেসমেন্ট, মুভমেন্ট লিমিটেশন, নিউরোলজিক্যাল ফাইন্ডিংস এবং ব্যক্তিগত ফাংশনাল গোল অনুযায়ী স্ট্রাকচারড রিহ্যাবিলিটেশন প্রদান করে।

আজই বুক করুন আপনার অ্যাপয়েন্টমেন্ট

দীর্ঘদিনের কবজির ব্যথা, দুর্বলতা বা হাতের অন্যান্য উপসর্গকে গ্রিপিং, টাইপিং, লিফটিং বা দৈনন্দিন কাজকে সীমাবদ্ধ করতে দেবেন না। সঠিক অ্যাসেসমেন্টের মাধ্যমে উপসর্গের সম্ভাব্য উৎস চিহ্নিত করে উপযুক্ত রিহ্যাবিলিটেশন পরিকল্পনা করা সম্ভব।

কবজির ব্যথা এবং সংশ্লিষ্ট হাত ও আপার লিম্ব সমস্যার পেশাদার ফিজিওথেরাপি অ্যাসেসমেন্ট ও রিহ্যাবিলিটেশনের জন্য ADPORC-এ যোগাযোগ করুন।

Carpal Tunnel Syndrome: Symptoms and Physiotherapy Treatment

Carpal Tunnel Syndrome: Symptoms and Physiotherapy Treatment

Median nerve compression can cause tingling, numbness and difficulty using the hand.

Read more
De Quervain’s Tenosynovitis: Thumb-Side Wrist Pain

De Quervain’s Tenosynovitis: Thumb-Side Wrist Pain

Thumb-side wrist pain may increase with gripping, twisting and lifting.

Read more
Trigger Finger: Finger Catching and Locking

Trigger Finger: Finger Catching and Locking

A related hand condition that affects finger movement rather than the wrist itself.

Read more
Wrist Drop: Radial Nerve and Wrist Extension

Wrist Drop: Radial Nerve and Wrist Extension

A neurological presentation with difficulty actively lifting the wrist.

Read more

Asia Digital Physiotherapy & Orthopedic Rehabilitation Center Asia Digital Physiotherapy & Orthopedic Rehabilitation Center Asia Digital Physiotherapy & Orthopedic Rehabilitation Center